A surgeon at Winship Cancer Institute of Emory University has performed Georgia’s first robotic nipple-sparing mastectomy outside a clinical trial, bringing a new minimally invasive surgical option to select patients with breast cancer.
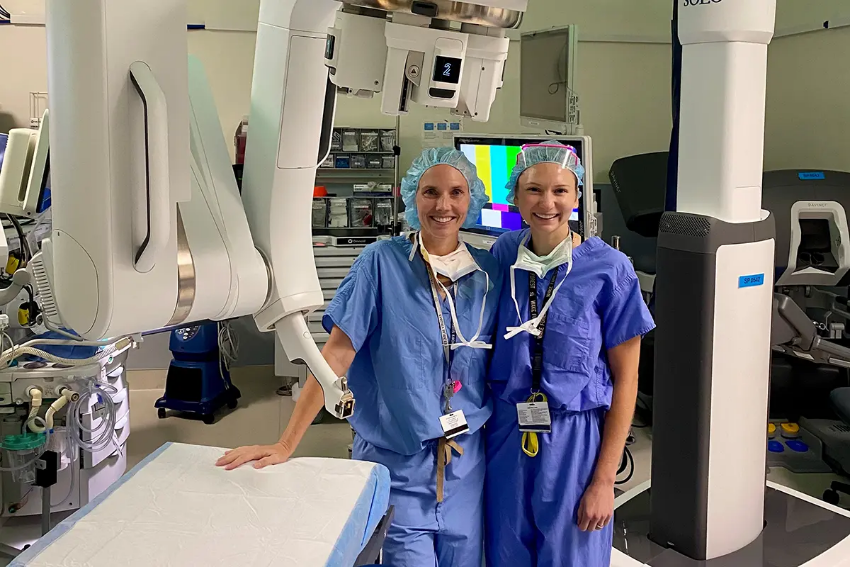
Clara Farley, MD, a breast surgical oncologist at Winship, performed the procedure at Emory Saint Joseph’s Hospital. Farley previously served as Emory’s site principal investigator for the national clinical trial evaluating the robotic surgical approach.
“This is an exciting new frontier in breast surgery,” says Farley, who is also a researcher in Winship’s Cancer Prevention and Control Research Program and assistant professor in the Department of Surgery at Emory University School of Medicine.
A different approach to nipple-sparing surgery
Nipple-sparing mastectomy removes breast tissue while preserving the nipple, areola and much of the natural breast skin. Compared with a traditional mastectomy, the procedure can support a more natural-looking result after reconstruction and offer potential benefits for body image and quality of life.
Winship surgeons already perform nipple-sparing mastectomies using a conventional open approach. Robotic nipple-sparing mastectomy accomplishes the same primary surgical goal but changes how the surgeon accesses and removes the breast tissue.
During conventional nipple-sparing surgery, the surgeon removes breast tissue through an incision made on or beneath the breast. The robotic approach allows the surgeon to perform the operation through a smaller, more discreetly placed incision, often along the outer breast or near the underarm.
Using a magnified, three-dimensional view and flexible robotic instruments, the surgeon can work precisely within the confined space between the breast tissue and overlying skin. The technology is designed to improve surgical access and visualization while allowing gentler handling of the breast skin and nipple areolar complex.
“The robotic platform allows us to work through a small, strategically placed incision with enhanced visualization in a confined space,” Farley says. “For appropriately selected patients, this approach may offer meaningful advantages in sensation, appearance and reconstruction while preserving the nipple-areolar complex and much of the natural breast skin.”
Potential benefits include less visible scarring, better preservation of skin sensation, and cosmetic and reconstructive advantages, although additional research is needed to evaluate these potential benefits over time.